
Doptelet provides a rapid and durable platelet count lift that lasts1*†
Pivotal trial:
Primary Endpoint: Patients on Doptelet obtained a platelet response for a median of 12.4 cumulative weeks without the need for rescue therapy.1‡§II
Secondary Endpoint:
Image
Secondary Endpoint:
Image
Day 8 Platelet Count ≥50x109/L1¶
Image
Core study (pivotal trial)
Efficacy was evaluated in a 6-month, multicenter, randomized, double-blind, placebo-controlled Phase 3 study. Patients had received one or more prior chronic ITP therapies and had average screening and baseline platelet counts of <30×109/L. Forty-nine patients were randomized (2:1) to receive either Doptelet (n=32) or placebo (n=17).1
- The primary efficacy endpoint was the cumulative number of weeks of platelet response, defined as a platelet count ≥50×109/L in the absence of rescue therapy, over 6 months of once-daily treatment in adults with chronic ITP. Doptelet-treated patients had a median duration of 12.4 cumulative weeks vs 0 weeks for placebo1
- A secondary efficacy endpoint was the proportion of patients with a platelet response (platelet counts ≥50×109/L) at Day 8. 66% (n=21/32) of Doptelet-treated patients had platelet counts of ≥50,000/μL at Day 8 compared to placebo (n=0/17)1
Open-label extension
Patients could enter the open-label extension phase if they completed the 6-month core study, or if they experienced a lack of efficacy during that period. In the extension phase, all patients received titrated Doptelet once daily. Thirty-nine patients (24 Doptelet and 15 placebo) entered the 90-week maintenance period of the extension phase, in which Doptelet dose titration and downward titration of concomitant ITP medications were allowed. At the end of the extension phase, a 4-week, dose-tapering period was followed by a 30-day follow-up after the last dose of Doptelet.3,4
- The primary endpoint of the extension study was to assess the long-term safety and efficacy of treatment with Doptelet by measuring platelet response rate, bleeding, and the use of rescue therapy3
- The secondary efficacy endpoint included the percentage of patients who achieved platelet counts ≥50,000/μL or ≥100,000/μL at any time during the core study and its extension phase. These endpoints were reported in an integrated analysis of the Phase 3 core study and extension phase data. In an integrated analysis of the core study and its extension phase, 93.8% of patients initially randomized to Doptelet and who continued to be treated with Doptelet during the extension phase achieved a platelet count of ≥50,000/μL at any time, compared to 64.7% of placebo patients who rolled over to Doptelet2,4
Post hoc analysis
This post hoc analysis assessed the endpoints from the Phase 3 study and provided previously unreported data on the percentage of patients who were able to achieve a platelet response or complete response at any time during the core study and extension phase.2
Limitations and disclosures*
- The open-label extension was not placebo-controlled; therefore, causality cannot be attributed, and hypothesis testing cannot determine whether within-arm changes were due to drug effect. This data is not included in the Doptelet Prescribing Information
- There is no comparator in the post hoc analysis, and further studies are needed to validate these results. The post hoc analysis is not included in the Doptelet Prescribing Information, and the FDA did not consider this analysis in approving Doptelet
Platelet counts over time
A durable platelet response was observed.1*†
Exploratory endpoint: Mean platelet count from baseline to 6 months for Doptelet-treated vs placebo-treated patients5
Image
Image
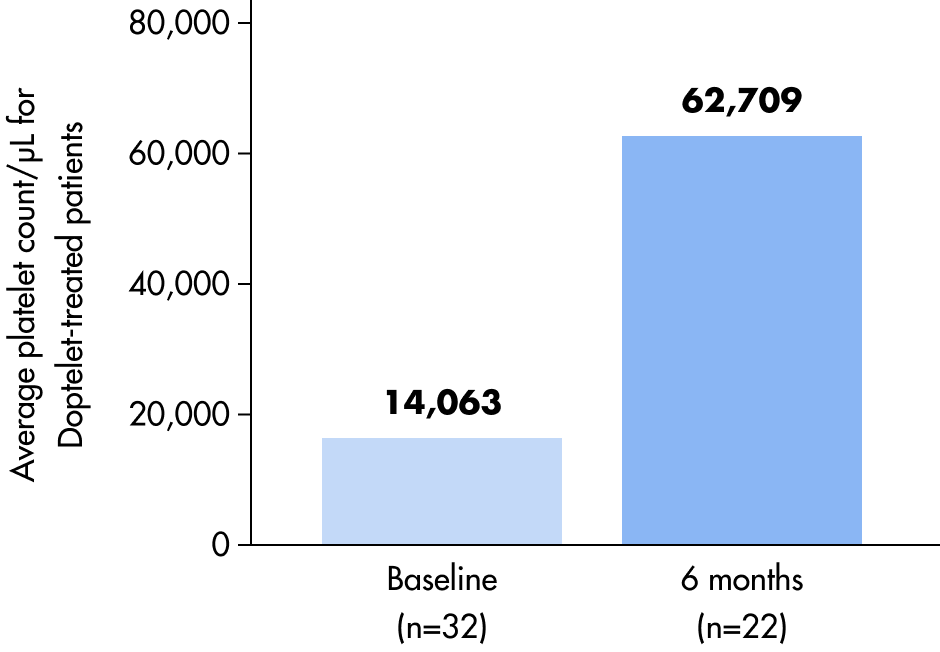
Placebo-treated patients
Seventeen patients that received placebo entered with a mean platelet count of 12,712/μL.
One placebo patient finished the core study with a mean platelet count of 31,000/μL.5
Important disclaimers: This exploratory endpoint is not included in the Doptelet Prescribing Information. The results of this exploratory endpoint may differ from those observed in clinical practice.
*The major efficacy outcome in this trial was the cumulative number of weeks in which the platelet count was ≥50×109/L during the 6-month treatment period in the absence of rescue therapy. 66% of patients treated with Doptelet were able to achieve a platelet count of ≥50x109/L in as few as 8 days.1
†The durable platelet response rate was significantly greater in avatrombopag-treated patients compared with those receiving placebo (34.4% vs 0.0%; P=0.009).3
‡Throughout the core study and extension phase, 72.3% of patients were exposed to avatrombopag for at least 32 weeks. In the open-label extension phase for those patients continuing Doptelet treatment, a response was achieved at 44.2% of visits.3,4
§After initiating therapy with Doptelet, assess platelet counts weekly until a stable platelet count of 50x109/L has been achieved, and then obtain platelet counts monthly thereafter. Obtain platelet counts weekly for at least 4 weeks following discontinuation of Doptelet.1
IIPlatelet response is a platelet count of ≥50,000/μL, and complete response is a platelet count of ≥100,000/μL.2
¶Patient platelet counts at baseline in the Doptelet-treated group were ≤15x109/L (56.3%), 15-30x109/L (40.6%), and ≥30x109/L (3.1%).3
FDA=Food and Drug Administration; ITP=immune thrombocytopenia.
Post hoc analysis:
Platelet response across the core and extension study2#**
Across the core study and open-label extension, Doptelet continued to support platelet response in most patients.
94% of patients treated with Doptelet achieved a platelet response at any time.
Image
Image
See how Dr Nagalla interprets these results from the Doptelet clinical trial
The healthcare professional in this video has been compensated by Sobi for these discussions; however, the views expressed during this video may reflect personal opinions and experiences of the healthcare professional. Any patient cases discussed represent individual cases and are not representative of every patient's treatment journey. Individual results may vary.
Observed platelet response based on prior TPO-RA use6#
In a post hoc analysis of the Phase 3 trial, platelet response with Doptelet was evaluated in relation to prior TPO-RA use, and the outcomes were:
- 38% of patients treated with Doptelet had been on a previous TPO-RA therapy
- Comparable efficacy was observed, with median cumulative weeks of platelet counts ≥50×109/L being 12.7 in patients with prior TPO-RA use (n=12) and 12.4 in those without prior TPO-RA use (n=20)
- Up to 6 months of Doptelet exposure in the trial
Median cumulative weeks with platelet response in Doptelet-treated patients by TPO-RA treatment history6
This analysis evaluated platelet response duration in patients previously treated with a TPO-RA versus those who were TPO-RA naive, offering insight into Doptelet performance across different treatment backgrounds.
Image
Image
A proportion of Doptelet-treated patients achieved a similar platelet response by Day 8 regardless of previous TPO-RA use6#
Important disclaimers: This post hoc analysis may not meet the FDA definition of an adequate and well-controlled study. Results from this analysis may differ from those observed in clinical practice. This analysis is not included in the Doptelet Prescribing Information and the FDA did not consider it in approving Doptelet.
#Platelet response is a platelet count of ≥50,000/μL, and complete response is a platelet count of ≥100,000/μL.2
**Results are comprised of patients who were initially randomized to Doptelet in the core study.5
††In an integrated analysis of the core study and its open-label extension phase, 93.8% of patients initially randomized to Doptelet achieved a platelet count of ≥50,000/µL at any time, and 64.7% of placebo patients who rolled over to Doptelet in the open-label extension phase also reached this metric.2
FDA=Food and Drug Administration; TPO-RA=thrombopoietin receptor agonist.
REAL-AVA 3.5 study:
Data in patients initiating treatment with Doptelet7
A multicenter analysis was conducted in the largest real‑world US cohort of adult patients with primary ITP who changed from eltrombopag (ELT) or romiplostim (ROMI) to Doptelet (N=201).
The platelet response to Doptelet was the proportion of patients who achieved at least one meaningful platelet count threshold of ≥30×109/L, ≥50×109/L, or ≥100×109/L in the absence of rescue therapy7‡‡
The durability of response was the percentage of time patients maintained at least one platelet count above these response thresholds while on Doptelet without the need for rescue therapy7‡‡
Platelet response
Almost all patients on Doptelet with baseline platelet counts <30×109/L achieved response levels ≥30×109/L.7
For patients who changed from ELT to Doptelet7:
- 100% (53/53) achieved a platelet response ≥30×109/L
- 99% (67/68) achieved a platelet response ≥50×109/L
- 59% (54/92) achieved a platelet response ≥100×109/L
For patients who changed from ROMI to Doptelet7:
- 96% (25/26) achieved a platelet response ≥30×109/L
- 91% (41/45) achieved a platelet response ≥50×109/L
- 62% (42/68) achieved a platelet response ≥100×109/L
For all patients who initiated Doptelet (N=201), the median change in platelet counts from baseline was 46.0×10⁹/L (Q1–Q3: 23.0–92.0).8
Durability of response
Durability of platelet response was high for patients on Doptelet7:
- Responders (200/201) spent a median 94% of time ≥30×109/L
- Responders (196/201) spent a median 90% of time ≥50×109/L
- Responders (136/201) spent a median 67% of time ≥100×109/L
Response durability was also high among patients with baseline platelet counts <30×109/L7:
- Responders (78/79) spent a median 92% of time ≥30×109/L
- This study was a retrospective chart analysis, and participating physicians were volunteers, limiting generalizability
- Platelet counts were collected during routine care (non-standardized timing)
- Adverse events were not systemically collected, and safety was inferred from dose changes or discontinuations
Are you an HCP with additional questions? Click here to talk with a Medical Science Liaison (MSL).
‡‡Platelet count observations obtained during or immediately following rescue therapy were not included in the response analysis if they fell within the following time periods after rescue therapy: platelet transfusions (1 week), intravenous immunoglobulin (IVIG) or anti-D immunoglobulin (4 weeks), and immunosuppressants or steroids (8 weeks).7
The Doptelet safety data
Review adverse events and key safety takeaways from clinical use.
Image
- DOPTELET (avatrombopag) [prescribing information]. Morrisville, NC: AkaRx, Inc; 2025.
- Nagalla S, Vredenburg M, Tian W, Allen LF. Platelet response to avatrombopag in patients with chronic immune thrombocytopenia: additional analyses from a phase 3 study and its extension. Blood. 2019;134(suppl 1):1071.
- Jurczak W, Chojnowski K, Mayer J, et al. Phase 3 randomised study of avatrombopag, a novel thrombopoietin receptor agonist for the treatment of chronic immune thrombocytopenia. Br J Haematol. 2018;183(3):479-490.
- Al-Samkari H, Aggarwal K, Vredenburg M, Tian W, Allen LF. Long-term response rates in patients with chronic immune thrombocytopenia treated with avatrombopag: additional analyses from a phase 3 study and its extension phase. Blood. 2019;134(suppl 1):2356.
- Data on file. 302 clinical study report. 2016: Sobi, Inc.
- McCrae KR, Allen LF, Aggarwal K, Vredenburg M, Tian W, Kuter D. Poster presented at: ISTH Conference 2019. Abstract PB0416.
- Piatek C, Oladapo A, Kolodny S, et al. Real-world treatment patterns and outcomes among patients with immune thrombocytopenia (ITP) who switched treatment from eltrombopag or romiplostim to avatrombopag in the United States: Results from the REAL-AVA 3.5 study. Br J Haematol. 2026;208(6):2185-2193.
- Data on file. 2026: Sobi, Inc.